



HBOT for Sensorineural Hearing Loss in Singapore
Sudden sensorineural hearing loss is one of the most time-critical conditions in ENT medicine. Patients often wake up with hearing markedly reduced or absent in one ear, sometimes with tinnitus or a sense of fullness. The instinct is to wait and see. The correct response is to get assessed urgently, because the treatment window closes quickly.
This guide explains what sudden sensorineural hearing loss is, how it is treated, where HBOT fits as an adjunct, and what the evidence supports. For broader context, see our complete guide to hyperbaric oxygen therapy and our HBOT evidence grading guide.
What Is Sudden Sensorineural Hearing Loss (SSNHL)?
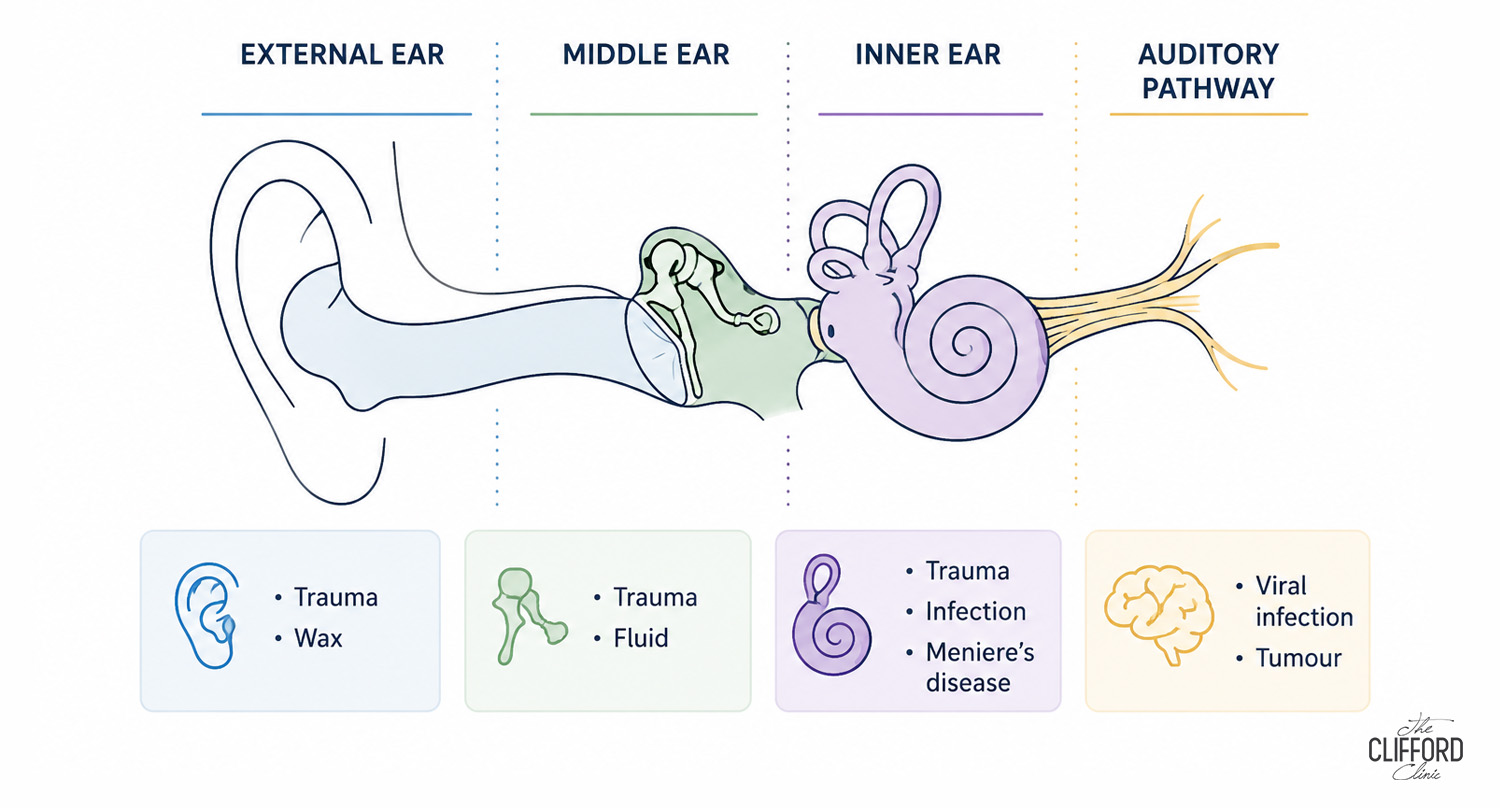
Sudden sensorineural hearing loss, often abbreviated SSNHL, is the rapid onset of hearing loss involving the inner ear or auditory nerve, usually in one ear. Most clinical definitions describe it as a hearing drop of 30 decibels or more across three connected frequencies, occurring over 72 hours or less. The cause in any individual case is usually unclear, although vascular, viral and inflammatory mechanisms have all been proposed.
It is genuinely an ENT emergency. The longer the inner ear remains compromised, the lower the chance of meaningful recovery. Some patients recover spontaneously, but many do not and the chance of recovery falls steadily over the first few weeks.
Sudden Hearing Loss Treatment: Why the 14-Day Window Matters
The most important aspect is timing. The strongest evidence for any treatment of SSNHL (steroids or HBOT) exists in the first two weeks after symptom onset, with the best outcomes seen when treatment starts within days. After two weeks, the chance of meaningful recovery drops considerably, and beyond about a month it is much lower again.
This is why the correct response to sudden hearing loss in one ear, with no obvious explanation like wax or infection, is not to wait. It is to see an ENT specialist as soon as possible.
Steroid Treatment for Sudden Sensorineural Hearing Loss
The first-line treatment for SSNHL in most settings is corticosteroid therapy, given orally or by intratympanic injection (directly into the middle ear, where it can reach the inner ear at higher concentrations). The exact protocol depends on the ENT specialist and the patient. Steroids alone produce recovery in a meaningful proportion of patients, particularly when started promptly.
HBOT is not the first-line treatment. It is most usefully considered as an adjunct alongside steroids, or as a second-line option when steroids alone have not produced the desired response.
How Hyperbaric Oxygen Therapy Treats Sensorineural Hearing Loss
The inner ear has a high oxygen demand and a single small blood supply. Damage to that supply or to the cells it feeds is thought to be one mechanism behind SSNHL. HBOT raises plasma oxygen, which can reach the cochlea via the fluids that bathe the inner ear, and may help support cells that are stressed but not yet permanently damaged. There may also be a role in dampening the inflammatory response.
Mechanistic plausibility does not, on its own, guarantee a clinical benefit. The judgement on HBOT for SSNHL is made on the clinical trials and reviews, not on theory alone.
Does Hyperbaric Oxygen Therapy Work for Hearing Loss? The Evidence
Sudden sensorineural hearing loss is listed among the Undersea and Hyperbaric Medical Society’s recognised indications for HBOT. Multiple randomised trials and meta-analyses suggest that HBOT, added to standard steroid treatment, improves hearing recovery in selected patients, particularly those with severe hearing loss who present early.
The evidence is not equally strong for mild hearing loss, or for patients who present after the early window. As with most conditions, HBOT works better in the cases that fit the supporting research.
Sudden Sensorineural Hearing Loss Recovery: What to Expect After HBOT
Even with optimal early treatment, some patients with SSNHL do not recover fully. Adding HBOT improves the odds in the right cases, but it does not guarantee a return to normal hearing. The honest framing for patients is that prompt steroid plus HBOT in a recognised window provides the best chance of meaningful recovery, while still preserving the patient’s autonomy to decide.
Patients are best served by an ENT specialist who explains the realistic chance of recovery for their specific situation, rather than a clinic that promises restoration.
Hyperbaric Oxygen for Idiopathic Sudden Sensorineural Hearing Loss: Use Cases
| Use or Claim | Evidence Tier | How We Talk About It |
|---|---|---|
| SSNHL Within 2 Weeks of Onset | Supported | Adjunct to steroid therapy, best outcomes when started early. |
| SSNHL 2–4 Weeks After Onset | Supported | Considered case-by-case, lower expected response. |
| SSNHL More Than 4 Weeks After Onset | Emerging | Evidence weaker, not routinely recommended. |
| Chronic Age-Related Hearing Loss | Wellness | Not an HBOT indication. |
| Tinnitus Without Hearing Loss | Wellness | Not a supported indication on its own. |
HBOT for Hearing Loss in Singapore: Referral, Sessions and Cost
In Singapore, the typical pathway starts when the patient notices sudden hearing loss in one ear, urgently sees a primary care doctor or ENT specialist, undergoes hearing assessment (typically pure tone audiometry), and is started on appropriate steroid therapy. HBOT is then added in selected cases, either at a hospital-based hyperbaric service such as Singapore General Hospital’s Hyperbaric and Diving Medicine Centre, or in coordinated arrangements with ENT specialists.
If sudden hearing loss is happening now, the most important step is to see an ENT specialist as soon as possible, not to research clinics online. For broader background on HBOT in Singapore, see our pillar guide on hyperbaric oxygen therapy in Singapore.
| MediSave and MediShield Life note
Sudden sensorineural hearing loss is not currently on MOH’s published list of approved HBOT indications, so MediSave and MediShield Life support is not generally available, even when HBOT is clinically appropriate. Sessions are typically paid out of pocket. Time matters far more than cost optimisation. Do not delay ENT assessment. |
Idiopathic Sudden Sensorineural Hearing Loss: The Clifford Clinic Approach
The Clifford Clinic’s clinical team’s first message about sudden sensorineural hearing loss is the same as every responsible ENT specialist’s. It is an emergency, and the patient should be assessed by an ENT specialist immediately. The clinic’s role is not to be the first point of contact for SSNHL. It is to support the ENT-led plan when HBOT has been recommended as an adjunct.
Where the clinic adds value is in the practical delivery of an HBOT course alongside the ENT plan. Patients with SSNHL referred for HBOT often need to attend daily or near-daily sessions across the early window after onset, which is the period where the evidence is strongest. A hard-shell chamber at a therapeutic 2.0 ATA, doctor-led screening by a clinician, and a Raffles Place location that makes intensive scheduling realistic for working patients are all designed to make that schedule achievable.
The team is also honest with patients about what HBOT can and cannot promise. Across four years and more than 200 patients, the clinic’s experience and the published evidence agree. HBOT added to steroid therapy in the early window improves the chance of meaningful recovery, but it does not guarantee complete restoration of hearing. Patients who present later or with very mild loss should expect a more modest benefit.
The clinical team’s guiding principle is that the best clinical outcome in SSNHL comes from an ENT specialist leading care, prompt steroid treatment, and HBOT added in the right window when appropriate, not from any one clinic acting alone. That is the path the clinic supports.
HBOT for Sudden Hearing Loss: Frequently Asked Questions
Is sudden hearing loss really an emergency?
Yes. The chance of meaningful recovery falls quickly over the first few weeks, so urgent assessment by an ENT specialist is important.
Should I see an ENT before considering HBOT?
Yes. SSNHL needs urgent ENT assessment and is usually treated first with steroid therapy. HBOT, where appropriate, is added by referral.
How soon does HBOT need to start?
The strongest evidence is for treatment started in the first two weeks after onset. The earlier, the better.
How many sessions are usually needed?
Protocols vary but often span 10 to 20 sessions, scheduled close together. Your hyperbaric clinician will set the protocol.
Does HBOT work for old hearing loss?
No. HBOT for SSNHL targets the early treatment window. Chronic, long-standing hearing loss does not respond to HBOT.
Will I get all my hearing back?
Not always. Even with optimal treatment, some patients do not fully recover. HBOT improves the odds in the right cases without guaranteeing a result.
Will MediSave or MediShield Life cover this?
Sudden sensorineural hearing loss is not currently on MOH’s published list of approved HBOT indications, so sessions are typically paid out of pocket. Confirm current MOH guidance before treatment.
Is HBOT safe with steroid treatment?
Generally yes, when supervised. Your treating ENT specialist and hyperbaric clinician will coordinate the plan.
What causes sudden sensorineural hearing loss?
In most cases no cause is found, which is why it is often called idiopathic sudden sensorineural hearing loss. Vascular, viral and inflammatory mechanisms affecting the cochlea or auditory nerve have all been proposed. ENT assessment first rules out treatable causes such as wax or infection.
Is hyperbaric oxygen therapy a recognised treatment for hearing loss?
Sudden sensorineural hearing loss is listed among the Undersea and Hyperbaric Medical Society’s recognised indications for HBOT, as an adjunct to steroid therapy. It is not on MOH’s approved indication list in Singapore, so MediSave and MediShield Life do not apply.
Can HBOT help if sudden hearing loss started more than 2 weeks ago?
Between two and four weeks after onset, HBOT is considered case by case with a lower expected response. Beyond four weeks the evidence is weaker and it is not routinely recommended.
Does HBOT help tinnitus that comes with sudden hearing loss?
Tinnitus often accompanies SSNHL and may improve as hearing recovers. Tinnitus without hearing loss is not a supported HBOT indication on its own.
Key Research on Hyperbaric Oxygen and Sensorineural Hearing Loss
- Undersea and Hyperbaric Medical Society. Hyperbaric Oxygen Therapy Indications, 13th Edition — sudden sensorineural hearing loss.
- Lamm K, Lamm H, Arnold W. Effect of hyperbaric oxygen therapy on inner ear vascular conditions. Advances in Otorhinolaryngology.
- Bennett MH et al. Hyperbaric oxygen for idiopathic sudden sensorineural hearing loss and tinnitus. Cochrane Database of Systematic Reviews.
- Kirby JP et al. Essentials of Hyperbaric Oxygen Therapy: 2019 Review. Missouri Medicine.
- Singapore General Hospital. Hyperbaric and Diving Medicine Centre — services and conditions treated.
- Mayo Clinic. Hyperbaric oxygen therapy: overview and indications.

If you are experiencing sudden hearing loss, please see an ENT specialist immediately. To discuss adjunct HBOT once you have been assessed, book a consultation at The Clifford Clinic.

Author Bio
Dr Gerard Ee

Dr Gerard Ee is the Founder and Managing Director of The Clifford Clinic in Singapore. He earned his medical degree from St George's University of London and built his surgical experience across the Singapore General Hospital, National University Hospital, and Mount Sinai Hospital in New York. He holds Membership of the Royal College of Surgeons (Edinburgh) and a Postgraduate Diploma in Dermatology (Cardiff), and is fully accredited in aesthetic procedures including botulinum toxin, fillers, lasers, and light therapies. A strong advocate of minimally invasive, natural-looking results, Dr Ee has published in several medical and scientific journals and presented his research in cities including Taipei, Las Vegas, and London.
See all posts by Dr Gerard Ee »