



Botox for Iliopsoas Syndrome, Psoas Spasm and Snapping Hip
Quick answer. Botox (botulinum toxin type A), injected into the iliopsoas under ultrasound guidance, may relieve deep groin or hip pain caused by psoas spasm. It may also reduce a painful internal snapping hip when an overactive psoas tendon is responsible. Evidence is limited and comes mainly from spasticity and mixed myofascial pain studies, so treatment is reserved for resistant cases that have not improved with conservative care.
Medically reviewed by Dr Gerard Ee of The Clifford Clinic, Singapore. Last updated July 2026.
The iliopsoas is the body’s most powerful hip flexor. It runs deep from the lumbar spine and inner pelvis to the top of the thigh bone. Persistent overactivity or spasm can cause poorly localised pain in the groin or front of the hip, and the source may be missed for months. The same muscle tendon unit can also produce an internal snapping hip. In carefully selected cases, reducing its activity directly may relieve symptoms.
What iliopsoas syndrome is
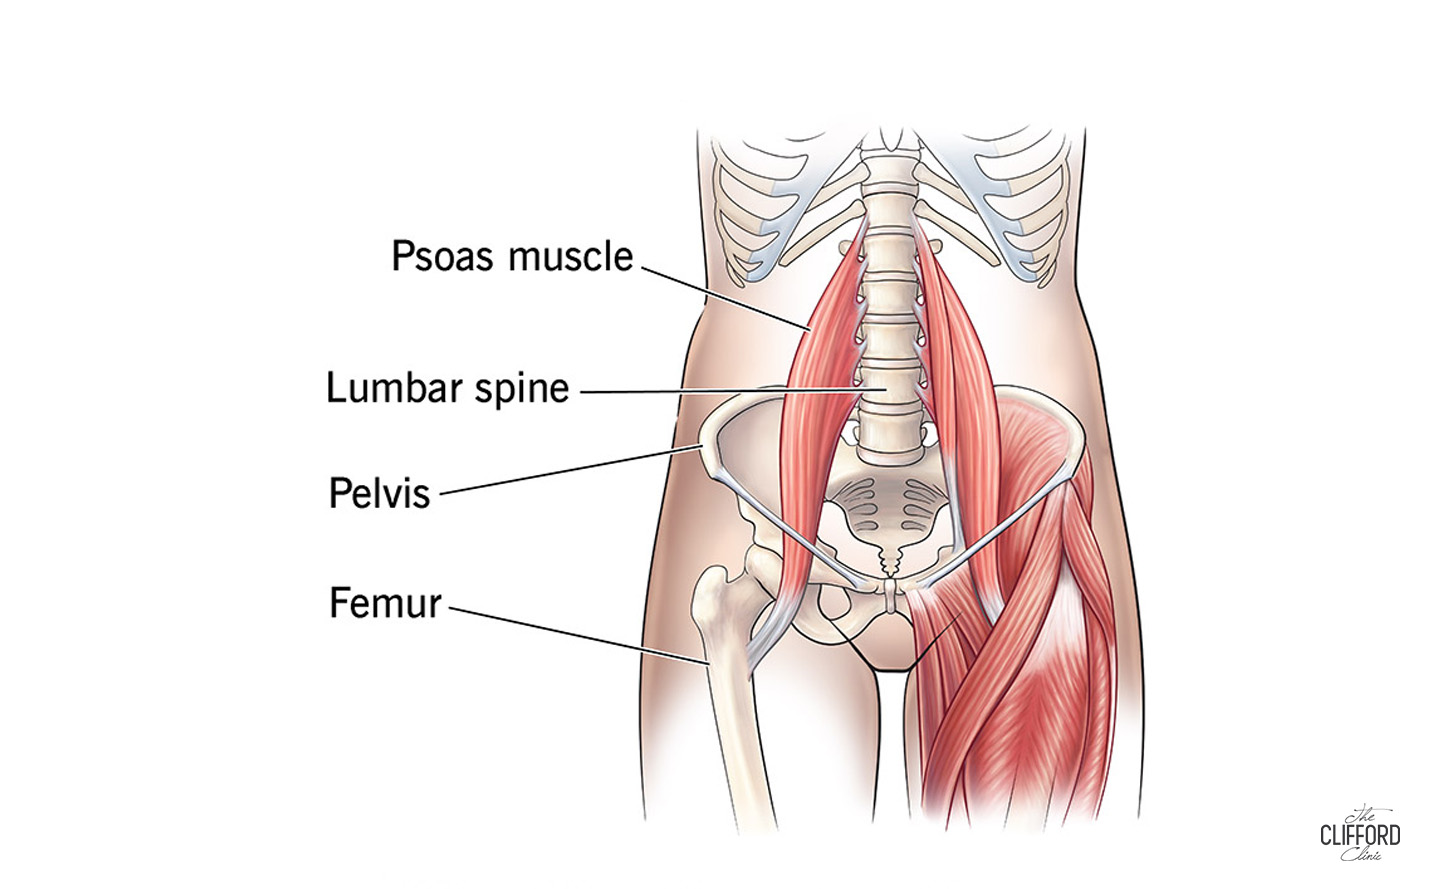
Iliopsoas syndrome covers several related problems involving the muscle and tendon. The tendon or the bursa beneath it may become irritated. The psoas muscle may remain in painful spasm. Or the tendon may flick over a bony ridge in the pelvis, causing an internal snapping hip. Symptoms include deep pain at the front of the hip or groin, pain when lifting the knee or rising from a chair, and clicking or catching during movement.
Why the iliopsoas causes pain
The iliopsoas crosses both the lumbar spine and the hip so that persistent overactivity can affect a large part of the movement chain. Spasm keeps the tendon under tension against the pelvic brim, which can produce snapping and irritate the underlying bursa. Trigger points may refer pain into the groin, front of the thigh or lower back. Symptoms can therefore resemble or coexist with lumbar and hip joint problems.
Why conventional treatments sometimes fall short
Initial treatment includes relative rest, activity changes, targeted physiotherapy and suitable medication. An image guided steroid injection into the iliopsoas bursa may also help when inflammation is prominent. Many patients improve. Resistant cases are harder because the muscle lies too deep for consistent manual treatment, while steroid injection does not directly reduce muscle overactivity. If spasm and snapping continue despite rehabilitation, reducing resting muscle tone may be considered.
How Botox works for iliopsoas syndrome
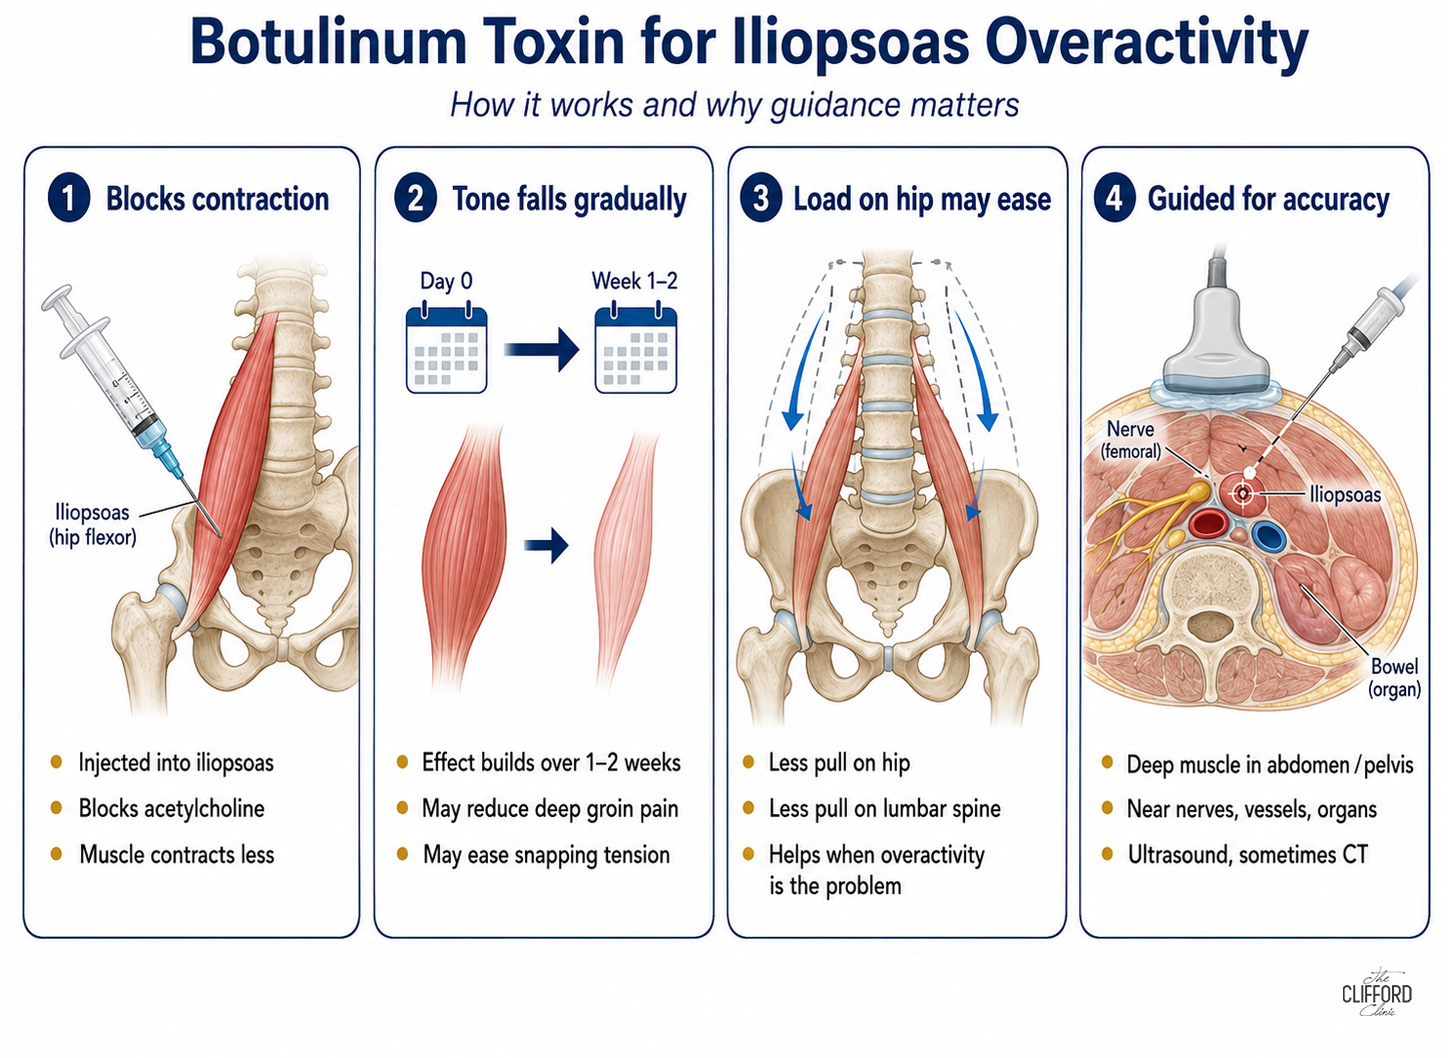
Botulinum toxin blocks the release of acetylcholine, the chemical signal that makes a muscle contract. After injection into the iliopsoas, resting tone falls over one to two weeks. This may reduce deep groin pain and the tension that makes the tendon snap over the pelvis. The pull on the lumbar spine and hip may also ease. Because the muscle lies deep in the abdomen and pelvis near important nerves, blood vessels and organs, ultrasound, and occasionally CT, is used to guide placement.
What the evidence shows
Evidence for botulinum toxin in the iliopsoas is limited. Stronger studies come from spasticity, particularly in children with cerebral palsy, where injections reduce muscle tone and improve hip movement. A myofascial pain trial that included the iliopsoas reported better later pain relief with botulinum toxin than with steroid injection. Neither setting directly represents isolated, non spastic iliopsoas syndrome or snapping hip. Treatment is therefore a targeted option for selected resistant cases, and may be considered before surgery rather than as routine first line care.
The psoas is deep, so we inject it under ultrasound guidance. When it is targeted accurately, the relief can be quick, and we pair it with physiotherapy to retrain the hip.
Dr Dinesh Sirisena, Consultant in Sports and Exercise Medicine, The Clifford Clinic
For a snapping hip that keeps returning, botulinum toxin is a reasonable and reversible step to try before an operation. If a scan shows a structural cause that surgery would treat better, we discuss that openly.
Dr Gerard Ee, Medical Director, The Clifford Clinic
The need for ultrasound guidance
Image guidance is essential for iliopsoas injection. The muscle lies deep to the abdominal contents and close to the femoral nerve, major blood vessels, kidney and bowel. Ultrasound allows the clinician to see the muscle and needle in real time, confirm placement and avoid surrounding structures. Anatomical studies also inform the safest route and target within the muscle.
Botulinum toxin as a step before surgery for snapping hip
When painful internal snapping hip does not improve with rehabilitation, surgery to release or lengthen the iliopsoas tendon may be considered. Surgery can help, but it involves recovery and carries a risk of persistent weakness or incomplete relief. Botulinum toxin offers a temporary, less invasive step. A good response also supports the iliopsoas as the source of the symptoms. The snapping may return as the treatment wears off if rehabilitation has not addressed the underlying problem.
Who may benefit, and who should avoid treatment
Psoas Botox Treatment: Who May Benefit
| May Benefit | Should Avoid or Delay |
|---|---|
| Deep groin or hip pain from psoas spasm resistant to physiotherapy | Pregnancy or breastfeeding |
| Painful internal snapping hip from an overactive psoas tendon | Neuromuscular disease such as myasthenia gravis |
| Recurrent symptoms despite steroid injection and rehabilitation | Infection at or near the injection site |
| Preference to try a less invasive step before surgery | Allergy to botulinum toxin products |
Risks and side effects
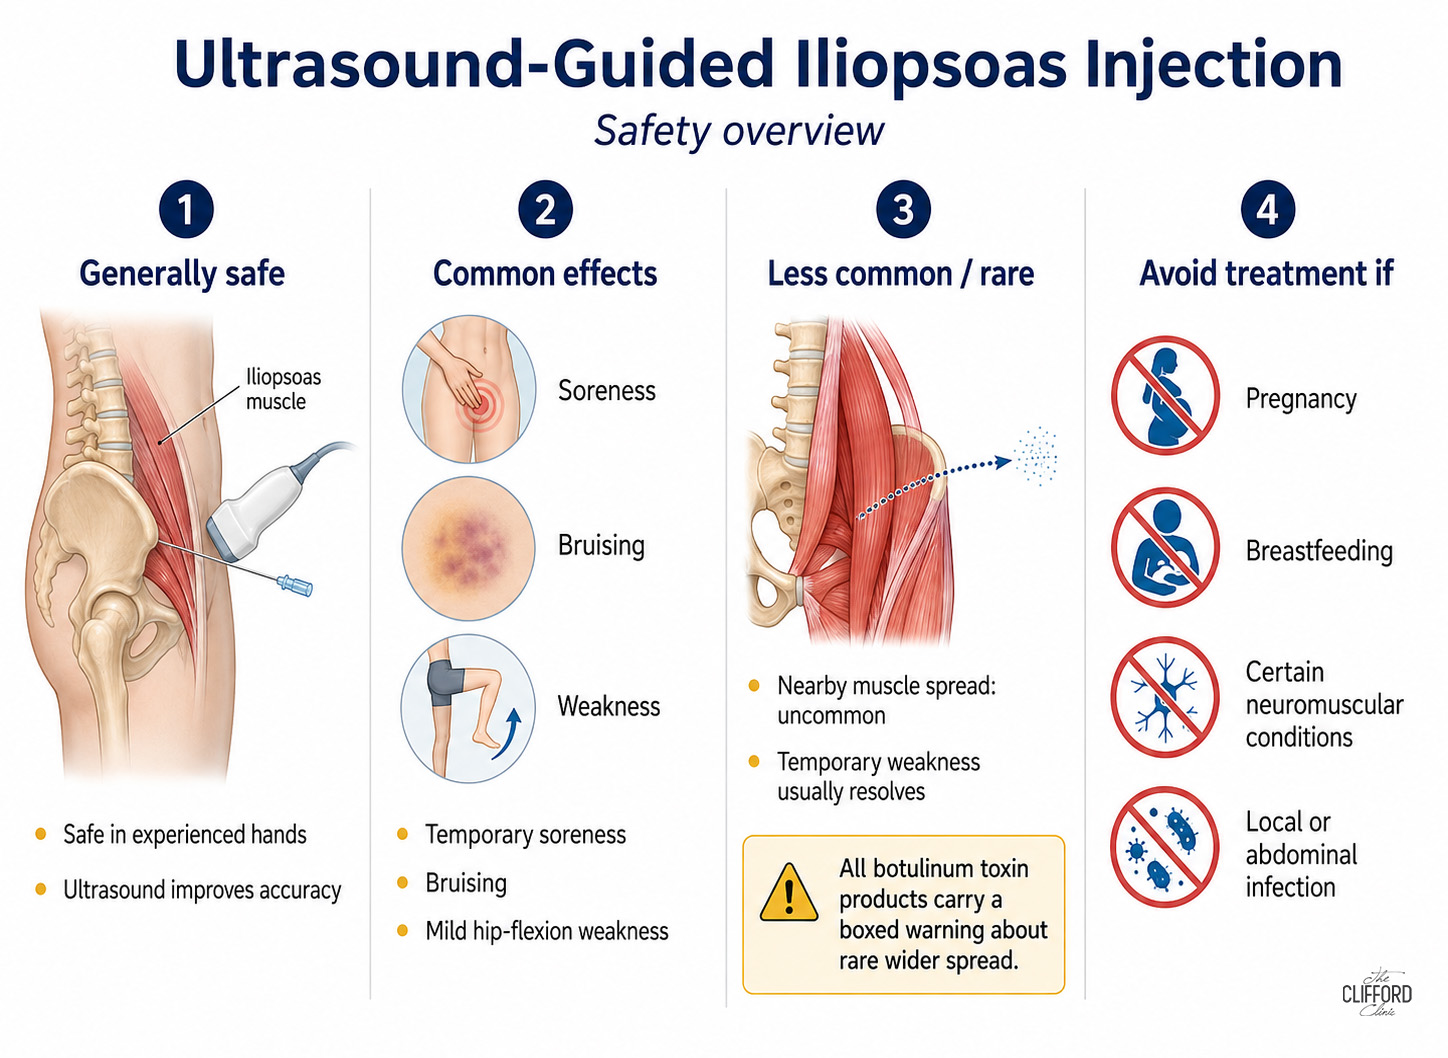
Ultrasound guided iliopsoas injection is generally safe in experienced hands. Temporary soreness, bruising and mild weakness in hip flexion are the most common effects. Spread to a nearby muscle is uncommon and causes weakness that resolves as the toxin wears off. All botulinum toxin products carry a boxed warning about the rare possibility of wider spread. Treatment is avoided during pregnancy and breastfeeding, in certain neuromuscular conditions and where there is a local or abdominal infection.
Clinical use for iliopsoas injection
Most published research on botulinum toxin in the iliopsoas comes from neurological conditions, including cerebral palsy, adult spastic hip deformity and stiff person spectrum disorder. In these settings, ultrasound guided injection can reduce hip region pain when muscle overactivity is a major cause. Cautious extrapolation to resistant iliopsoas tightness may be reasonable, particularly when knee or lower back symptoms coexist, although botulinum toxin has not shown a clear benefit in deep gluteal syndrome.
Because its effect is short lived, botulinum toxin can be both a diagnostic and a therapeutic tool for the iliopsoas. Relaxing the muscle relieves symptoms and confirms the source, and a longer term solution can then be planned. I like to obtain objective measures of tightness first so the benefit can be quantified.
Dr Dinesh Sirisena, Consultant in Sports and Exercise Medicine, The Clifford Clinic
Speak to our doctors

Botulinum toxin for muscle and joint pain is a considered, individualised treatment. To determine whether it is appropriate, arrange an assessment with the team at The Clifford Clinic or read more about the work of Dr Gerard Ee. The clinicians will review the history, perform an examination and explain the available options before any treatment is planned.
Frequently Asked Questions
Can botulinum toxin treat iliopsoas syndrome?
It may help selected patients by reducing iliopsoas spasm and overactivity. This can ease deep groin or hip pain and may reduce painful snapping. Evidence is limited and mainly indirect, so treatment is considered only after physiotherapy and other suitable measures have failed to provide lasting relief.
Can botulinum toxin help snapping hip?
It may help when an internal snapping hip is caused by an overactive iliopsoas tendon. Relaxing the psoas reduces the tension that makes the tendon move over the pelvis. In suitable cases, it offers a less invasive, reversible option before surgery.
Is ultrasound guidance needed for psoas injection?
Yes. The iliopsoas lies close to major nerves, blood vessels and organs. Ultrasound, or occasionally CT, is used to place the injection accurately and avoid surrounding structures.
How long does the effect last?
Relief develops over one to two weeks and usually lasts for about two to six months. Treatment may be repeated when appropriate. Physiotherapy during the period of reduced spasm aims to improve movement and reduce the chance of recurrence.
Does it cause weakness afterwards?
A mild, temporary reduction in hip flexion strength is expected because the psoas is a hip flexor. Strength returns as the treatment wears off, and rehabilitation helps maintain function during this period.
Related Conditions
Explore other articles in our series on botulinum toxin for musculoskeletal pain.
- Botox for Muscle Pain (main guide), the overview of botulinum toxin for musculoskeletal pain
- Botox for Lower Back Pain, chronic low back pain and lumbar muscle spasm
- Botox for Quadratus Lumborum Pain, stubborn one sided lower back spasm
- Botox for Tight Hip Flexors, anterior hip pain in runners and cyclists
- Botox for Gastrocnemius Tightness, calf tightness and cramps
- Botox for Plantar Fasciitis, chronic heel pain that resists other measures
- Botox for Trapezius and Shoulder Myofascial Pain, trapezius tightness and shoulder trigger points
Compare Treatments and Procedures
Compare the available treatments and what each procedure involves.
- Botox vs Steroid Injection, how the two injections differ and when each is chosen
- Botox vs PRP, muscle relaxation compared with tissue healing
- Botox vs Dry Needling, two trigger point options compared
- Ultrasound Guided Injections, why guidance matters for deep muscles
- Recovery and Physiotherapy after Botox, what to expect and how to get the most from treatment
More from The Clifford Clinic
Read about related treatments and services available at The Clifford Clinic.
- Platelet Rich Plasma Injections for Musculoskeletal Injury Recovery
- Botox for the Trapezius Muscle
- Botox Treatment for Cervical Torticollis
- Bioscaffold Therapy for Musculoskeletal Regeneration
- Hyaluronic Acid Injection for Knees
About the Authors

Dr Dinesh Sirisena is a Consultant in Sports and Exercise Medicine at The Clifford Clinic. He completed his sports and exercise medicine training in the United Kingdom and has cared for elite football, rugby, athletics and hockey teams, including at the London 2012 Olympic and Paralympic Games. He specialises in ultrasound guided injections and other non surgical treatments for muscle, tendon and joint pain, has led a musculoskeletal service as its medical director, and is an assistant professor at the NUS Yong Loo Lin and NTU Lee Kong Chian schools of medicine.

Dr Gerard Ee is the Medical Director of The Clifford Clinic. He trained at St George’s University of London and is a Member of the Royal College of Surgeons of Edinburgh, and built his orthopaedic experience at National University Hospital and Singapore General Hospital with a focus on the knee, joint and spine. He has published widely in peer reviewed orthopaedic and spine journals. You can also read more about his work at drgerardee.com.
Dr Dinesh Sirisena is a Consultant in Sports and Exercise Medicine at The Clifford Clinic. He trained in sports and exercise medicine in the United Kingdom and has worked with elite football, rugby, athletics and hockey teams, including at the London 2012 Olympic and Paralympic Games. He specialises in ultrasound guided injections and other non surgical treatments for muscle, tendon and joint pain. He has also led a musculoskeletal service as medical director and is an assistant professor at the NUS Yong Loo Lin and NTU Lee Kong Chian schools of medicine.
Selected orthopaedic and spine publications by Dr Gerard Ee
- Ee G, Srivastava A, Peng CWB, Tan SB, Tow BPB. Management of the neglected and healed bilateral cervical facet dislocation. European Spine Journal. 2014.
- Ee WWG, Lau WLJ, Yeo W, Yap VB, Yue WM. Does minimally invasive surgery have a lower risk of surgical site infections compared with open spinal surgery. Clinical Orthopaedics and Related Research. 2014.
- Ee G, Jiang L, Guo CM, Yeo W, Tan SB, Tow B, Chen J, Yue WM. Comparison of clinical outcomes and radiographic measurements in four treatment modalities for osteoporotic compression fractures. Journal of Spinal Disorders and Techniques. 2015.
- Ee G, Pang SY, Kumar N, Malhotra R. A silent acute abdomen in a patient with spinal cord injury. BMJ Case Reports. 2013.
References
- Myofascial pain syndrome, an update on clinical characteristics, etiopathogenesis, diagnosis and treatment. Muscle and Nerve. 2025.
- Neurobiological mechanisms of botulinum neurotoxin induced analgesia for neuropathic pain. Pharmacology and Therapeutics. 2024.
- The analgesic effects of botulinum neurotoxin by modulating pain related receptors, a literature review. Molecular Pain. 2024.
- Approved uses and prescribing information for botulinum toxin type A. United States Food and Drug Administration. 2024.
- Ultrasound guided botulinum toxin for hip pain in cerebral palsy. Toxins. 2023.
- Botulinum toxin as a diagnostic adjunct in adult spastic hip and knee. JBJS Reviews. 2026.
- Systematic review of analgesic botulinum toxin in cerebral palsy. Toxicon. 2021.
- Stiff person spectrum cohort with paraspinal and hip flexor injection. Therapeutic Advances in Neurological Disorders. 2025.
- Systematic review of botulinum toxin for deep gluteal syndrome. Journal of Bodywork and Movement Therapies. 2022.
Medical disclaimer. This article is for general education and does not replace a consultation with a qualified doctor. Botulinum toxin for musculoskeletal pain is an individualised treatment that is off label for most of these conditions. Suitability, dosing and outcomes vary between people. Please seek an in person assessment at The Clifford Clinic before making any treatment decision.

Author Bio
Dr Gerard Ee

Dr Gerard Ee is the Medical Director of The Clifford Clinic in Singapore. He earned his medical degree from St George's University of London and built his surgical experience across the Singapore General Hospital, National University Hospital, and Mount Sinai Hospital in New York. He holds Membership of the Royal College of Surgeons (Edinburgh) and a Postgraduate Diploma in Dermatology (Cardiff), and is fully accredited in aesthetic procedures including botulinum toxin, fillers, lasers, and light therapies. A strong advocate of minimally invasive, natural-looking results, Dr Ee has published in several medical and scientific journals and presented his research in cities including Taipei, Las Vegas, and London.
See all posts by Dr Gerard Ee »