



Botox for Muscle Pain and Botulinum Toxin for Musculoskeletal Pain
Quick answer. Botulinum toxin (Botox) relaxes overactive muscles and calms pain signalling nerves. It is not approved for musculoskeletal pain, but off label use has real supporting evidence for some conditions, most notably chronic low back pain and plantar fasciitis, and a weaker, more indirect evidence base for others.
Medically reviewed by Dr Gerard Ee and Dr Dinish Sirisena of The Clifford Clinic, Singapore. Last updated July 2026.
Persistent muscle pain is among the most common reasons for seeking medical help and among the most difficult to treat when a muscle fails to relax. When a muscle remains in a state of permanent contraction, it compresses its own blood supply, irritates nearby nerves and forms tender trigger points. Analgesics, stretching and massage may provide relief for a few days, but the tightness always returns. For a selected group of patients, botulinum toxin injection offers a different approach. Rather than masking the pain, it reduces the muscle overactivity that contributes to it and appears to quieten the nerves that transmit pain.
What botulinum toxin is, and what it is approved for
Botulinum toxin type A is a purified protein. In the small, controlled doses used in medicine it has an established safety record over several decades. It is formally approved for conditions such as chronic migraine, cervical dystonia and various forms of spasticity. It is not approved for most musculoskeletal pain conditions, so its use for muscle and joint pain is off label. Off label use does not imply that a treatment is unproven or unsafe. It indicates that an established medicine is being used for a purpose outside its licensed indications, on the basis of the available evidence and clinical judgement.
How botulinum toxin relieves pain
The analgesic effect of botulinum toxin extends beyond muscle relaxation, which explains its efficacy in pain that does not respond to conventional muscle relaxants.
Evidence-based reviews have examined botulinum toxin type A in several non-cosmetic head and neck conditions associated with involuntary muscle activity or pain. These include cervical dystonia, masticatory myalgia, temporomandibular disorders and bruxism.6,7 The same reviews found high-level evidence that botulinum toxin was ineffective for chronic neck pain, illustrating why a benefit demonstrated for one diagnosis should not automatically be applied to another pain condition.
Effects around the muscle
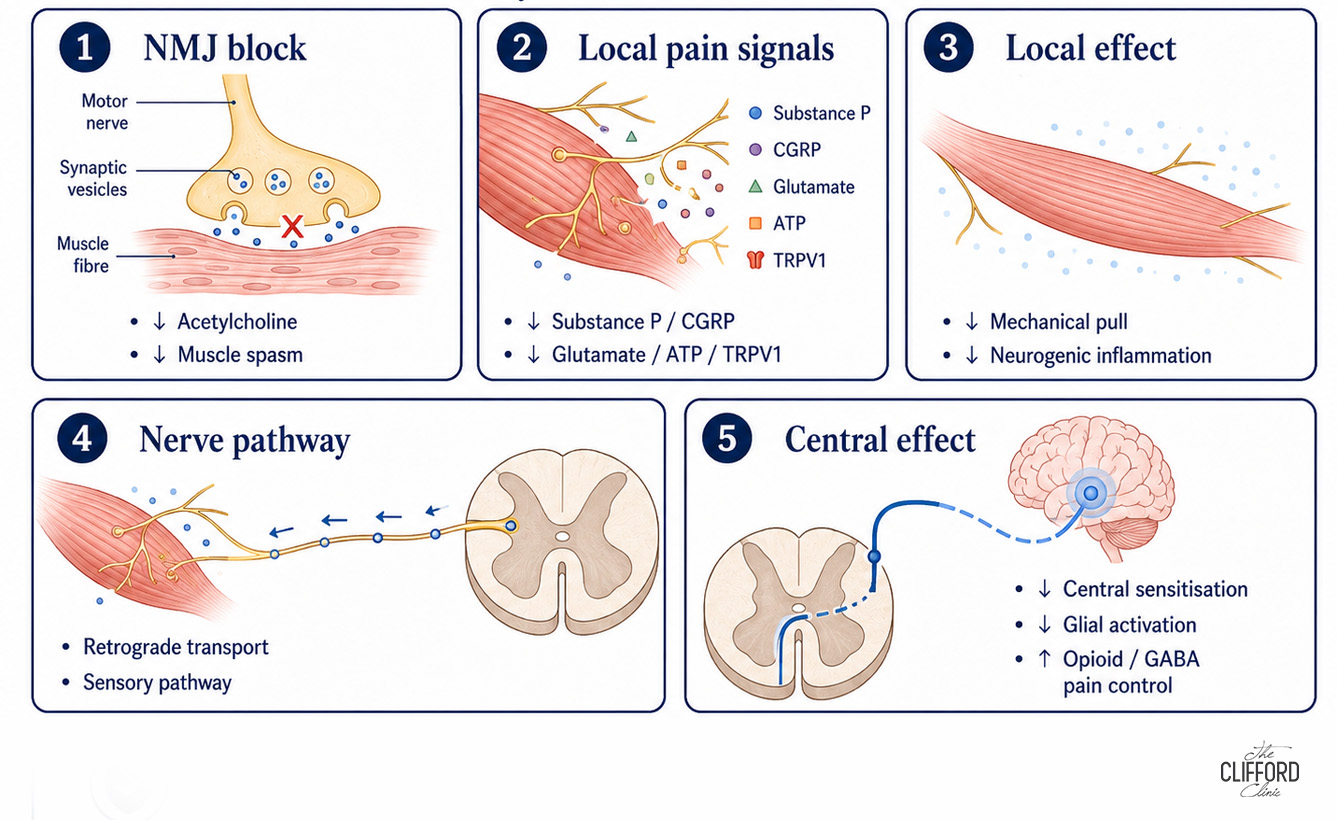
At the junction between nerve and muscle, botulinum toxin blocks the release of acetylcholine, the chemical signal that tells a muscle to contract. The treated muscle therefore contracts less and gradually relaxes, which eases spasm and reduces the mechanical pull on tendons, joints and trigger points. Alongside this, the toxin reduces the release of pain-sensitising messengers from local nerve endings. This includes chemicals like substance P, calcitonin gene-related peptide, glutamate and ATP, and it turns down pain receptors such as TRPV1. It also reduces the movement of other pain receptors to the nerve surface.
By lowering these signals, it also calms the low-grade nerve-driven inflammation that keeps a painful area sensitive.
Effects on the nervous system
After injection, some of the toxin is carried back along the nerve to the sensory nerve cell bodies and into the spinal cord. There, it appears to reduce the release of pain messengers from incoming nerves and to settle the amplified pain state known as central sensitisation. It also calms the supporting glial cells that help maintain chronic pain, and it appears to strengthen the body’s natural pain control through the opioid and GABA systems. These central actions are one reason the relief from a single treatment can be broader and longer lasting than the muscle weakening alone would predict.
Why muscle tightness causes pain
A healthy muscle contracts when needed and relaxes fully afterwards. In chronic conditions this reset fails. Overuse, posture, past injury, nerve irritation or protective guarding around a sore joint can leave a muscle partly contracted around the clock. That constant tension reduces local blood flow and starves the tissue of oxygen. It forms taut bands and trigger points that refer pain elsewhere. Muscle tension and prolong contraction also overloads the tendons the muscle pulls on and can press on nearby nerves. Pain then causes more guarding, guarding causes more tightness and the cycle sustains itself.
Why conventional treatments sometimes fall short
First line care, including activity change, physiotherapy, stretching, oral painkillers, medicines that reduce inflammation and sometimes steroid or anaesthetic injections, helps most people and should almost always be tried first. The limitation is that these measures do not switch off the excessive muscle activity itself. Oral muscle relaxants act on the whole body and often cause drowsiness before they meaningfully relax the target muscle. Steroid injections reduce inflammation but not muscle overactivity, and repeated steroid use carries tissue risks. Dry needling and manual therapy can release trigger points, but in stubborn cases the relief is brief. Botulinum toxin is considered when muscle overactivity is a clear part of the problem and standard care has not been enough.
Conditions covered in this series, and how strong the evidence is
The strength of the evidence varies considerably between conditions, and this is stated plainly below.
Botox for Pain: Evidence by Condition
| Condition | What the Evidence Looks Like |
|---|---|
| Chronic Low Back Pain | Moderate. Pooled trials show meaningful pain and function gains over placebo, with benefit that tends to fade over time. |
| Plantar Fasciitis | Good. Pooled randomised trials show clear pain relief and better function, sustained for months. |
| Myofascial Pain in Specific Muscles | Modest. Helpful for some well-defined trigger points, with durability that can exceed steroids. |
| Iliopsoas and Hip Flexor Pain | Limited. Mostly from spasticity and mixed myofascial studies rather than isolated hip flexor pain. |
| Quadratus Lumborum Pain | Very limited. No high-quality trials isolate this muscle. Use rests on mechanism and wider back pain data. |
| Gastrocnemius, Calf Tightness | Very limited outside spasticity. No specific trials in non-spastic calf tightness. |
In summary, botulinum toxin is not a first-line treatment or a universal remedy. It is a targeted option for carefully selected patients with muscle overactivity that has resisted standard care, and it is most effective as part of a rehabilitation plan rather than in isolation. The individual condition guides are listed in Related Reading.
How treatment is carried out

Treatment begins with a consultation and examination to confirm that a specific overactive muscle is driving the pain. The doctor identifies the target muscle, plans the dose and injection points, and cleans the skin. Using a fine needle, small amounts of botulinum toxin are placed into the muscle, often at several points to spread the effect. For deep or complex muscles such as the psoas, injections are guided by ultrasound so the needle and target are seen in real time and nearby structures are avoided. The injections themselves take only a few minutes.
Evidence from jaw-related musculoskeletal pain also shows why treatment comparisons need to be interpreted carefully. A 2025 systematic review and meta-analysis of six studies compared botulinum toxin injections with occlusal splints in people with temporomandibular disorders. There was no statistically significant overall difference in maximum mouth opening and no significant difference in graded chronic pain between the treatments.9
Different botulinum toxin type A preparations have product-specific potency units, clinical evidence and dosing protocols. A systematic review of lower urinary tract treatment assessed onabotulinumtoxinA and abobotulinumtoxinA separately.8 The units or doses used for one preparation, anatomical area or indication should therefore not be transferred directly to another.
Research in other organs further illustrates this need for indication-specific treatment. A 2025 study in children with achalasia examined botulinum toxin injection into the lower oesophageal sphincter together with balloon dilatation and compared the outcomes with historical controls who received balloon dilatation alone.10 The study involved gastrointestinal motility rather than painful skeletal muscle, so its doses, results and safety findings cannot be applied directly to musculoskeletal injections.
Maximum mouth opening favoured botulinum toxin at the one-week assessment and occlusal splints at three months, while outcomes were similar at six months and longer follow-up. These findings concern the temporomandibular joint and masticatory system and should not be extrapolated directly to lower back, hip flexor, calf, shoulder or plantar fascia pain.
Botox for Pain: Evidence by Condition
| Condition | What the Evidence Looks Like |
|---|---|
| Chronic Low Back Pain | Moderate. Pooled trials show meaningful pain and function gains over placebo, with benefit that tends to fade over time. |
| Plantar Fasciitis | Good. Pooled randomised trials show clear pain relief and better function, sustained for months. |
| Myofascial Pain in Specific Muscles | Modest. Helpful for some well-defined trigger points, with durability that can exceed steroids. |
| Iliopsoas and Hip Flexor Pain | Limited. Mostly from spasticity and mixed myofascial studies rather than isolated hip flexor pain. |
| Quadratus Lumborum Pain | Very limited. No high-quality trials isolate this muscle. Use rests on mechanism and wider back pain data. |
| Gastrocnemius, Calf Tightness | Very limited outside spasticity. No specific trials in non-spastic calf tightness. |
Selecting between botulinum toxin, platelet-rich plasma and a steroid
The appropriate injection depends on the problem, and at The Clifford Clinic the selection follows a clear rationale. For pain driven by muscle tightness, botulinum toxin is usually the first choice, since it targets the overactivity directly. For a tendon or fascia disorder such as plantar fasciitis, platelet-rich plasma is usually the first step, since the objective is to support healing. For certain tendon conditions, such as trigger finger or De Quervain tenosynovitis, a steroid is the appropriate first line, and for tennis elbow or golfer’s elbow a steroid is often used first with platelet-rich plasma held in reserve. Botulinum toxin is frequently combined with physiotherapy, orthoses, platelet-rich plasma, prolotherapy or Tenex, and where a tight muscle recurs, it can help a patient avoid surgical release.
If the indication is right, botulinum toxin can be extremely effective. For muscle tightness it is my first choice, whereas for a tendon or fascia problem I usually start with platelet rich plasma.
Dr Dinesh Sirisena, Consultant in Sports and Exercise Medicine, The Clifford Clinic
Botox will not fix a slipped disc. When a scan shows severe damage that surgery would treat better, I say so plainly. But where the pain is coming from tight muscle that has not settled despite plenty of physiotherapy and stretching, it can work very well.
Dr Gerard Ee, Medical Director, The Clifford Clinic
Who may benefit, and who should avoid treatment
The ideal candidate has already undertaken a substantial course of physiotherapy and stretching without resolution of the pain. Injection is not advised where imaging demonstrates severe structural damage that would be better treated by surgery, in which case an operation is the stronger option from the outset.
Botox for Pain: Suitability and Caution Guide
| May Benefit | Should Avoid or Use Caution |
|---|---|
| Chronic Muscle or Myofascial Pain Resistant to Physiotherapy | Infection at the injection site |
| A Clearly Identifiable Overactive Target Muscle | Known allergy to botulinum toxin products |
| Chronic Low Back Pain or Plantar Fasciitis After Failed Conservative Care | Neuromuscular disease such as myasthenia gravis or Lambert Eaton syndrome |
| Muscle Tightness and Pain Related to Spasticity | Pregnancy and breastfeeding, where it is generally avoided |
Risks and side effects
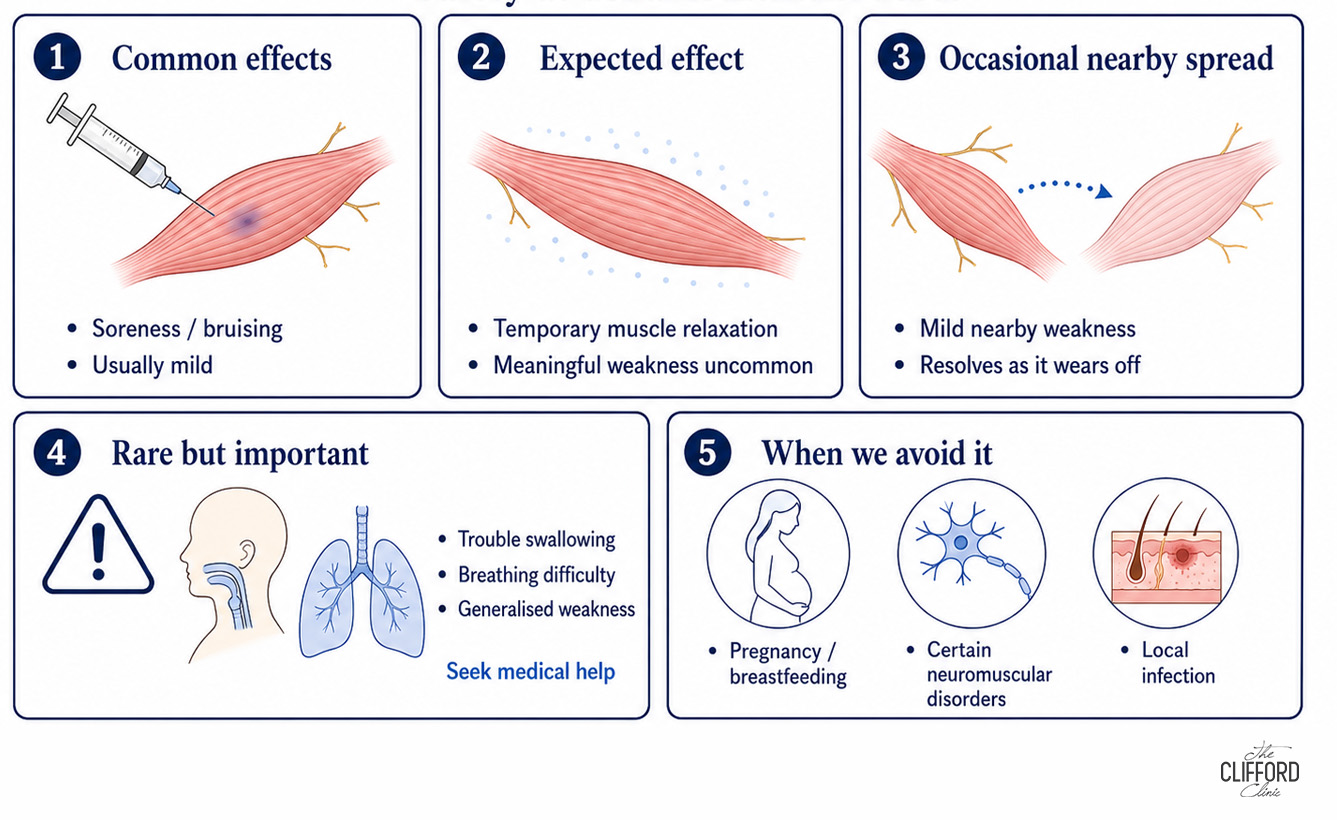
At the doses used for musculoskeletal pain, botulinum toxin has a reassuring safety record, and trials generally show no meaningful excess of adverse effects relative to control injections. The most common effects are temporary soreness or bruising at the injection site and mild, temporary weakness of the treated muscle, which is often the intended effect. Occasionally the effect spreads to a neighbouring muscle and produces mild weakness that resolves as the toxin wears off. Some patients experience brief flu like symptoms. Very rarely the effect can spread more widely and cause difficulty with swallowing or breathing or generalised weakness. This rare risk is the reason all botulinum toxin products carry a boxed warning, and it is why a full medical history is obtained and the lowest effective dose is used. In practice meaningful weakness is uncommon, because the muscles treated are large and already tense, so the dose relaxes them without producing weakness. Across clinical trials the adverse effects are usually mild and short lived, and only slightly more common than with a placebo injection. Treatment is avoided in pregnancy and breastfeeding, in certain neuromuscular disorders and where there is local infection.
An adjunct within a wider plan
Dr Dinesh Sirisena, the clinic consultant in sports and exercise medicine, regards botulinum toxin as an adjunct rather than a standalone treatment. In musculoskeletal and sports medicine the studies reporting hard, quantified success rates remain limited, and much of the benefit is assessed from the patient’s symptoms and function. Used appropriately, the injection unloads the underlying driver, usually muscle tightness, so that physiotherapy and other treatments can work more completely.
Botulinum toxin treatment of the trapezius has also attracted attention for aesthetic shoulder contouring. A 2024 publication examined the popular trend involving injections into the trapezius muscles.4 That literature concerns trapezius shape or hypertrophy rather than myofascial shoulder pain, so it should be interpreted separately from evidence assessing pain relief and physical function.
Published reports from other anatomical areas illustrate how unintended effects can depend on the injection site and spread to nearby or distant muscles. A 2024 case report described full upper-eyelid ptosis after facial aesthetic injections, while a 2019 case report described generalised botulism-like symptoms following treatment for axillary hyperhidrosis.2,3
A separate retrospective case series reported rare bilateral vocal-fold abductor paralysis after injections into the laryngeal muscles for adductor spasmodic dysphonia.5 These reports involved different anatomical areas and do not estimate the risk following ultrasound-guided musculoskeletal injections. They nevertheless reinforce the importance of anatomy-specific dosing and prompt medical assessment if unexpected generalised weakness, difficulty swallowing or breathing symptoms develop.
The clinic applies this thinking across four main areas, the calf in plantar fasciitis, the quadratus lumborum and paraspinal muscles in lower back pain, the iliopsoas in hip flexor tightness, and the trapezius and other muscles in myofascial and shoulder girdle pain. Botulinum toxin also features in shoulder girdle compression problems such as thoracic outlet and pectoralis minor syndromes, where relaxing the muscle can ease neurovascular symptoms.
Botulinum toxin is an adjunct, to be used alongside other treatments such as physiotherapy, platelet rich plasma and Tenex, to optimise pain and unload the underlying driver, usually muscle tightness, so that recovery is more holistic.
Dr Dinesh Sirisena, Consultant in Sports and Exercise Medicine, The Clifford Clinic
Speak to our doctors

Botulinum toxin for muscle and joint pain is a considered, individualised treatment. To determine whether it is appropriate, arrange an assessment with the team at The Clifford Clinic or read more about the work of Dr Gerard Ee. The clinicians will review the history, perform an examination and explain the available options before any treatment is planned.
Frequently Asked Questions
Is botulinum toxin for muscle pain the same as botulinum toxin for wrinkles?
It is the same active protein, used differently. Aesthetic treatment targets small facial muscles with very small doses. Musculoskeletal treatment targets larger, deeper muscles, often with ultrasound guidance and different dosing.
Is it approved for muscle pain?
No. Botulinum toxin is approved for conditions such as chronic migraine, cervical dystonia and spasticity. Its use for muscle and joint pain is off label, which means an established medicine used for a purpose outside its licensed indications, on the basis of the evidence and clinical judgement.
How long does it take to work, and how long does it last?
Most patients notice relaxation within several days, with the fuller effect by approximately four weeks. Relief usually lasts two to six months, and up to twelve months in some plantar fasciitis cases, after which it may be repeated if effective.
Is physiotherapy still required?
Yes. Botulinum toxin creates a period of reduced muscle overactivity. Physiotherapy uses that period to retrain movement and build lasting improvement. The two are most effective in combination.
Is it safe to repeat?
Yes. Repeat treatment every few months is common and generally well tolerated. Appropriate intervals and the lowest effective dose reduce the small risk of a diminished response over time. The clinician reviews the response at each visit.
Related Conditions
Explore the rest of our botulinum toxin for musculoskeletal pain series.
- Botox for Lower Back Pain, chronic low back pain and lumbar muscle spasm
- Botox for Quadratus Lumborum Pain, stubborn one sided lower back spasm
- Botox for Tight Hip Flexors, anterior hip pain in runners and cyclists
- Botox for Iliopsoas Syndrome, psoas spasm and snapping hip
- Botox for Gastrocnemius Tightness, calf tightness and cramps
- Botox for Plantar Fasciitis, chronic heel pain that resists other measures
- Botox for Trapezius and Shoulder Myofascial Pain, trapezius tightness and shoulder trigger points
Compare Treatments and Procedures
Understand your options and what treatment involves.
- Botox vs Steroid Injection, how the two injections differ and when each is chosen
- Botox vs PRP, muscle relaxation compared with tissue healing
- Botox vs Dry Needling, two trigger point options compared
- Ultrasound Guided Injections, why guidance matters for deep muscles
- Recovery and Physiotherapy after Botox, what to expect and how to get the most from treatment
More from The Clifford Clinic
Related treatments and services offered at our clinic.
- Platelet Rich Plasma Injections for Musculoskeletal Injury Recovery
- Botox for the Trapezius Muscle
- Botox Treatment for Cervical Torticollis
- Bioscaffold Therapy for Musculoskeletal Regeneration
- Hyaluronic Acid Injection for Knees
About the Authors

Dr Dinesh Sirisena is a Consultant in Sports and Exercise Medicine at The Clifford Clinic. He completed his sports and exercise medicine training in the United Kingdom and has cared for elite football, rugby, athletics and hockey teams, including at the London 2012 Olympic and Paralympic Games. He specialises in ultrasound guided injections and other non surgical treatments for muscle, tendon and joint pain, has led a musculoskeletal service as its medical director, and is an assistant professor at the NUS Yong Loo Lin and NTU Lee Kong Chian schools of medicine.

Dr Gerard Ee is the Medical Director of The Clifford Clinic. He trained at St George’s University of London and is a Member of the Royal College of Surgeons of Edinburgh, and built his orthopaedic experience at National University Hospital and Singapore General Hospital with a focus on the knee, joint and spine. He has published widely in peer reviewed orthopaedic and spine journals. You can also read more about his work at drgerardee.com.
Together at The Clifford Clinic, our doctors have used botulinum toxin for muscle and joint pain for more than 16 years, performing around 100 of these treatments each year.
Selected orthopaedic and spine publications by Dr Gerard Ee
- Ee G, Srivastava A, Peng CWB, Tan SB, Tow BPB. Management of the neglected and healed bilateral cervical facet dislocation. European Spine Journal. 2014.
- Ee WWG, Lau WLJ, Yeo W, Yap VB, Yue WM. Does minimally invasive surgery have a lower risk of surgical site infections compared with open spinal surgery. Clinical Orthopaedics and Related Research. 2014.
- Ee G, Jiang L, Guo CM, Yeo W, Tan SB, Tow B, Chen J, Yue WM. Comparison of clinical outcomes and radiographic measurements in four treatment modalities for osteoporotic compression fractures. Journal of Spinal Disorders and Techniques. 2015.
- Ee G, Pang SY, Kumar N, Malhotra R. A silent acute abdomen in a patient with spinal cord injury. BMJ Case Reports. 2013.
Clinical Evidence and Safety Considerations for Botulinum Toxin in Muscle Pain
Botulinum toxin type A temporarily reduces acetylcholine release from selected nerve endings, decreasing activity in the injected muscle. Evidence-based reviews have examined its use in several non-cosmetic head and neck conditions associated with involuntary muscle contraction or pain, including cervical dystonia, masticatory myalgia, temporomandibular disorders and bruxism.6,7 The evidence differs considerably between conditions. The same reviews found stronger support for certain neuromuscular disorders than for non-specific chronic neck pain, which highlights the importance of establishing the cause of pain before considering treatment.
A 2025 systematic review and meta-analysis of six studies compared botulinum toxin injections with occlusal splints in people with temporomandibular disorders. Botulinum toxin was associated with greater maximum mouth opening at one week, while occlusal splints performed better at three months. The overall analysis found no statistically significant difference between the treatments in maximum mouth opening or graded chronic pain, particularly over longer follow-up.9 These findings apply to the temporomandibular joint and masticatory muscles and should not be extrapolated directly to lower back, hip flexor, calf, shoulder or plantar fascia pain.
Botulinum toxin preparations also have product-specific potency units, clinical evidence and dosing protocols. A systematic review of lower urinary tract treatment assessed onabotulinumtoxinA and abobotulinumtoxinA separately, illustrating why units or doses from one preparation should not automatically be transferred to another.8 The appropriate dose also depends on the muscle being treated, its size and function, the underlying diagnosis and the intended clinical outcome.
Research in other organs further demonstrates that botulinum toxin treatment is specific to the anatomical target and medical indication. A 2025 study in children with achalasia examined injections into the lower oesophageal sphincter together with balloon dilatation. The combination group showed greater improvement in several symptoms, growth measurements and radiological findings than historical controls who received balloon dilatation alone.10 This study involved gastrointestinal motility rather than painful skeletal muscle, so its dose, results and safety findings cannot be applied directly to musculoskeletal treatment.
Published literature has also examined botulinum toxin for aesthetic purposes. A 2024 publication reviewed the popular trend involving injections into the trapezius muscles for shoulder contouring.4 A separate 2025 randomised split-face study assessed botulinum toxin type A with or without an intradermal hyaluronic acid treatment for periorbital wrinkles. The combination-treated side had lower wrinkle-severity scores and higher satisfaction at selected follow-up points, while electromyography measurements did not differ significantly between the two protocols.1 These studies concerned appearance rather than pain relief and do not provide evidence that the same treatment approach will improve a painful muscle condition.
Potential adverse effects depend on the injection site, dose, treated muscle and whether the effect spreads to nearby or distant muscles. A 2024 case report described full upper-eyelid ptosis following facial aesthetic injections.2 Another case report described generalised botulism-like symptoms following treatment for axillary hyperhidrosis.3 A retrospective series also reported rare bilateral vocal-fold abductor paralysis after injections into the laryngeal muscles for adductor spasmodic dysphonia.5
These reports involved different anatomical areas and do not establish the incidence of complications following image-guided musculoskeletal injections. They nevertheless reinforce the importance of accurate diagnosis, knowledge of the relevant anatomy, preparation-specific dosing and prompt assessment of unexpected symptoms. Generalised weakness or difficulty speaking, swallowing or breathing requires urgent medical attention.
References
- Neves MLBB, Thome C, da Silva Junior SV, et al.
Efficacy and Durability of the Association of Botox and Skinvive in the Treatment of Moderate/Severe Wrinkles in the Periorbital Region: A Randomized, Controlled, Double-Blind, Split-Face Clinical Study.
Journal of Cosmetic Dermatology.
2025;24(8):e70403.
doi:10.1111/jocd.70403.
PMID: 40814769. - Musharbash IJ, Chakra RJ.
Treatment of Full Eyelid Ptosis Following Botox Injection: A Case Report.
Cureus.
2024;16(3):e55970.
doi:10.7759/cureus.55970.
PMID: 38476507. - Rouientan A, Alizadeh Otaghvar H, Mahmoudvand H, Tizmaghz A.
Rare Complication of Botox Injection: A Case Report.
World Journal of Plastic Surgery.
2019;8(1):116–119.
doi:10.29252/wjps.8.1.116.
PMID: 30873373. - Diaddigo SE, LaValley MN, Asadourian PA, Rohde CH.
“Barbie botox”: The systematic review of a popular trend.
Journal of Plastic, Reconstructive & Aesthetic Surgery.
2024;88:45–46.
doi:10.1016/j.bjps.2023.10.136.
PMID: 37952434. - Venkatesan NN, Johns MM, Hapner ER, DelGaudio JM.
Abductor paralysis after botox injection for adductor spasmodic dysphonia.
Laryngoscope.
2010;120(6):1177–1180.
doi:10.1002/lary.20855.
PMID: 20513036. - Persaud R, Garas G, Silva S, Stamatoglou C, Chatrath P, Patel K.
An evidence-based review of botulinum toxin (Botox) applications in non-cosmetic head and neck conditions.
JRSM Short Reports.
2013;4(2):10.
doi:10.1177/2042533312472115.
PMID: 23476731. - Awan KH.
The therapeutic usage of botulinum toxin (Botox) in non-cosmetic head and neck conditions: An evidence based review.
Saudi Pharmaceutical Journal.
2017;25(1):18–24.
doi:10.1016/j.jsps.2016.04.024.
PMID: 28223858. - Mangera A, Andersson KE, Apostolidis A, et al.
Contemporary management of lower urinary tract disease with botulinum toxin A: A systematic review of botox (onabotulinumtoxinA) and dysport (abobotulinumtoxinA).
European Urology.
2011;60(4):784–795.
doi:10.1016/j.eururo.2011.07.001.
PMID: 21782318. - İşisağ Ö, Atasoy H, Yıldız S.
Comparison of the effects of occlusal splint and Botox injections on the amount of mouth opening and chronic pain in individuals with temporomandibular disorders: A systematic review and meta-analysis.
Australian Dental Journal.
2025;70(2):132–140.
doi:10.1111/adj.13059.
PMID: 39953753. - Dara N, Aghaei M, Hosseini A, et al.
Efficacy of esophageal balloon dilatation with Botox injection in children with achalasia referred to a tertiary care center.
Scientific Reports.
2025;15:31228.
doi:10.1038/s41598-024-81781-5.
PMID: 40854912.

Author Bio
Dr Gerard Ee

Dr Gerard Ee is the Medical Director of The Clifford Clinic in Singapore. He earned his medical degree from St George's University of London and built his surgical experience across the Singapore General Hospital, National University Hospital, and Mount Sinai Hospital in New York. He holds Membership of the Royal College of Surgeons (Edinburgh) and a Postgraduate Diploma in Dermatology (Cardiff), and is fully accredited in aesthetic procedures including botulinum toxin, fillers, lasers, and light therapies. A strong advocate of minimally invasive, natural-looking results, Dr Ee has published in several medical and scientific journals and presented his research in cities including Taipei, Las Vegas, and London.
See all posts by Dr Gerard Ee »